
The Work · Works and Constellation
Turning Toward ADHD
Removing the Persona, and the Shadow You Can Never Quite Pin Down
This essay opens with crisis resources, and so does this page. If you are struggling, you are not alone, and reaching out is a strength rather than a weakness. If someone is in immediate danger, call 911.
988 Suicide & Crisis Lifeline — call or text 988, or chat at 988lifeline.org. Free, confidential, 24 hours a day.
Crisis Text Line — text HOME to 741741.
SAMHSA National Helpline — 1-800-662-4357. Free, confidential treatment referral, 24/7, in English and Spanish. Facility locator at findtreatment.gov.
CHADD — chadd.org. Home of the National Resource Center on ADHD, with clinician and local-chapter directories.
ADDA — add.org. An organization for adults with ADHD, with peer support groups and resources.
NAMI HelpLine — 1-800-950-6264, Monday to Friday, for information and support.
Outside the US, the Find A Helpline directory lists free, confidential lines by country. More are gathered on the Turning Toward page.
A piece on removing the persona, and on the shadow you can never quite pin down. Under Jung’s line that no one becomes conscious of the shadow without considerable moral effort, it turns toward ADHD in three registers, each marked on the page with a register seam: what the author lived, what he watched in others, and what the literature reports, cited at the back. It takes the medication question honestly (the pill as dragon, as lever, and finally as band-aid), and asks plainly that no one put down a prescription because of an essay. It then sets out the author’s own picture of the mind, a mirrored scale drawn as an hourglass with the present moment at its crossing, marked as a philosophical figure and not a clinical model, and closes on a finding about children, the calendar, and who gets diagnosed, before a note on the seams that makes no clinical claim.
Read the essay ↓ Download the PDF ↓ Cite this work (DOI) →
Part of the open Legible Traces archive — every piece free under CC BY 4.0. The PDF here is byte-for-byte the record deposited on Zenodo; the DOI is the canonical citation.
Turning Toward ADHD
For the clinicians, counselors, and staff of Children’s Mercy Kansas City, who meet children where they are.
This is an essay in the philosophy of psychology. It is not therapy, it is not treatment, and it is not a clinical opinion, because I do not have one to give. I am a writer and a student, not a physician, psychologist, psychiatrist, or therapist, and nothing here has been reviewed or approved by anyone who is.
This piece talks about medication, so let me be as clear as I know how: never start, stop, adjust, skip, or reorganize a prescribed medication because of anything you read here. That conversation belongs to you and the person who prescribed it. And ADHD is diagnosed by a clinician, not by recognizing yourself in a stranger’s paragraph. If what follows sounds like your life, that is a reason to talk to someone qualified, not an answer.
Experienced · Observed · Studied
Experienced: lived, and I am the only witness. Observed: watched in others, with their details anonymized or left out. Studied: read in the literature, and cited at the back.
No one can become conscious of the shadow without considerable moral effort.
— C. G. Jung, Aion
Three ways of knowing
Every piece in this series marks how each claim is known, and this one uses all three. Experienced: I lived it, and I am the only witness. Observed: I watched it happen to someone else, and their details are anonymized or left out. Studied: I read it in the literature, and it is cited at the back.
You will see the boundaries marked as you go. I call them register seams. They exist because a metaphor that wanders into a clinic can do real harm, and because you deserve to know, at every moment, whether you are reading evidence or reading me.
The squirrel
Much like the other four I have walked through (depression, addiction, suicidal thoughts, anxiety), I have a theory. It is woven completely through my own experience, and it does not replace the opinion of a professional.
I want to open the door on my attention deficit and show you the squirrel that keeps running by and taking my attention.
Did you see it?
You get it, though.
I didn’t, for a long time. I have always thought in metaphors and symbols. That is why I have so many of them on hand to write these things, to be honest.
So where am I, at this point in time?
I have walked through some of the darkest shadows and come out the other side.
Unscathed?
No. Let me not say that. I kept bouncing back and forth between depression and anxiety, and then still ADHD. What I came out with was not an absence of damage. It was a way of reading it.
Register seam · Studied
Below this line I am reading, not remembering. Every claim is cited at the back.
The pill and the dragon
There is a thing I noticed about the drugs they prescribe for it. They have a half-life. Not only in the body. In the story.
Early on, the results can be extraordinary. Work. School. The people you love. And then, for some, the quiet starts costing more than it did.
Here I have to be careful, because this is exactly the place where a metaphor becomes a lie.
What the literature says is contested, and the mainstream finding deserves to go first. In one long-term follow-up of 108 children who had responded well to methylphenidate and were tracked for three to ten years, only three lost their response in a way nothing but tolerance could explain (Safer & Allen, 1989).1 Most people who do well on these medications keep doing well. That is the headline, and it is not mine to bury.
But there is an underdog in this literature, and I want to give it its due, because it is the reading that matches what I have watched.
A retrospective chart review of 166 children and adolescents, reported in a letter, found tolerance in roughly a quarter of them, and every one of those cases came from the group taking more than the recommended ceiling (Ross et al., 2002).2 A later review argues that tolerance is real, under-recognized, and under-reported, in part because the studies that would have counted it often enrolled only the people it hadn’t happened to (Handelman & Sumiya, 2022). And in adults, twelve months of methylphenidate has been shown to raise striatal dopamine transporter availability by about a quarter, which is at least a plausible mechanism for why the world without the medication can start to feel worse than it did before there was any (Wang et al., 2013).3
Whether the dose increases that do happen are tolerance, or growth, or a dose that was never quite right to begin with is still being argued. A systematic review published this year concluded that tolerance does not commonly develop, while conceding that most of the evidence it had to work with was weak (Smith et al., 2026).
I am not here to settle it. I am here to say that the argument exists, and that if you are living inside it, you are not imagining things.
The body registers the change. Sleep. Appetite. In the largest long-term follow-up, the young adults who had taken it ended up about an inch shorter on average, and more than that among those who took it most consistently (Swanson et al., 2017). Those are the quiet costs, and they should be watched.
And there is a ceiling, and the ceiling is real. The label on methylphenidate says daily doses above sixty milligrams are not recommended (U.S. Food and Drug Administration, 2025, Section 2). Past that wall a prescriber has other moves: pausing the medication under supervision (there is a name for this, a structured treatment interruption, sometimes called a drug holiday), optimizing the dose, or changing the molecule altogether.
I used to call that tolerance reduction balancing, before I ever learned it had a clinical name. I will keep my phrase, because it is mine and it says what I meant by it. But the words a doctor uses are the words worth asking for.
Everyone is different. There are people who take the smallest dose every day and never want for more. Under the controlled conditions of the largest children’s trial, only about one child in six was still on the same drug at the same dose after fourteen months, and on average the dose drifted upward, from about thirty milligrams a day to about thirty-four (Vitiello et al., 2001).4
Modest is not nothing.
It is also not a dragon.
The same lever
Reward is reward. The brain runs one currency through one circuit, and alcohol, and amphetamine, and the small hot pleasure of finally finishing something all pay into the same account. People who take these medications and find their focus describe a loop I recognize from the bottle in Turning Toward Addiction: the thing works, the working feels good, the feeling good asks for the thing.
That is the philosophy. Here is the fact, and the fact cuts against the philosophy, and I would rather print it than protect my own metaphor.
Treating ADHD does not appear to make addiction more likely. An early meta-analysis of six studies found roughly a two-fold reduction in later substance-use disorder among young people treated with stimulants (Wilens et al., 2003). A larger meta-analysis a decade later found neither protection nor added risk (Humphreys et al., 2013). And a study of nearly three million patients found that during the months they were actually taking their medication, men had 35 percent lower odds of an emergency visit for a substance-related problem, and women 31 percent lower (Quinn et al., 2017).
So when I say the pill reaches for the same lever as the bottle, I am describing the inside of my own head, and offering it in the hope that you find your own parallel there.
I am not saying: put down the pill.
Please do not put down the pill because of an essay.
The band-aid
I have called the pill a dragon and I have called it a lever, and both are unfair to it. So let me say what I actually think it is.
A band-aid.
I want to be careful with that word, because I have heard it used as an insult and I do not mean it as one. A band-aid is what stops the bleeding. Ask anybody who is bleeding.
But nobody has ever mistaken a band-aid for the whole of medicine.
The literature says this more plainly than I would have dared to. One trial takes as its starting premise that adult ADHD is left incompletely treated by medication alone; that is the reason the trial exists. Eighty-six adults, all already on medication, all still struggling. Half received cognitive behavioral therapy; half received relaxation training with educational support. On one clinician rating, the responders were 53 percent against 23. On another, 67 percent against 33.
And those who responded were still holding their gains at six months, and at twelve (Safren et al., 2010).
Read that last part again, because it is the whole argument.
The gains held.
That is the thing a pill cannot do. A pill works while it is in you. It wears off at a predictable hour and takes its gift back on the way out. A skill does not wear off. Nobody has ever had to re-dose a habit.
In children the shape of the finding is the same. In the largest trial of its kind, medication management alone and medication combined with behavioral treatment came out about even on the core symptoms: the drifting, the fidgeting, the interrupting. But in several of the areas standing around those symptoms (oppositional behavior, anxiety, reading, social skills, the relationship between a parent and a child), the combined approach did better than routine community care, and medication alone did not (MTA Cooperative Group, 1999).
And then there is the sentence I would put on the ceiling of every waiting room, so that people lying awake could read it.
The children in the combined group did as well on lower doses than the children on medication alone (MTA Cooperative Group, 1999).5
Go back to the ceiling. Sixty milligrams. The wall. Now notice what the other thing does to that wall. It moves you further away from it.
There is even a trial on the order of operations. Start children with a modest dose of behavioral treatment, and you arrive at better outcomes overall than you get by starting with the medication (Pelham et al., 2016), and at lower cost (Page et al., 2016).
Not instead of.
Only: not alone. And, wherever it can be managed, not first.
Register seam · Experienced
Above this line, evidence. Below it, only me, and this is the thing I most wanted to say.
So here is my theory. It is a theory. I have proven nothing.
The pill is a band-aid. Not a bad one, and not a lie. It closes the thing long enough that you can stop attending to the bleeding and start attending to the wound.
But a band-aid left on for thirty years does not heal anything. It keeps the wound out of the light. You learn to move around it. You tell yourself the arrangement is working, because nothing is dripping.
I should say exactly what I mean by the wound, because I am not claiming what you might think.
ADHD does not leave. It is not cured, not by therapy and not by hourglasses, and anyone who tells you otherwise is selling something. But the wound is not the ADHD. The wound is what a life builds around it, over decades, when nobody ever told you what you were working with.
That is the part that closes.
What closed it for me (and I can speak for exactly one person here) was everything else. Therapy. Sleep I stopped negotiating with. Work I could actually finish. People who told me the truth when it cost them something. A room arranged so the squirrel had fewer places to run. And yes, the meditation, and the hourglass, and the long stupid patience of learning to stand in one moment at a time.
I do not think the drugs are bad. I have never once thought that.
I think they are the first thing. And we have built a world that treats them as the only thing, and then we act surprised, years later, to find the wound still lying there, exactly where we left it.
And if the pill is all you have right now (because therapy costs money you do not have, or sits behind a waiting list nine months long, or lives in a city you cannot drive to), hear this before you turn the page. You are not doing it wrong. You are doing it with what you were handed.
The distance between what the guideline recommends and what an actual person can reach is not a personal failing. It is the subject of the last section of this essay, and it makes me angrier than anything else in it.
The persona
I said I would talk about me, so let’s talk about me.
I had walked through all those other doors and uncovered what seemed to be the root cause of most of them. The way I see it, the brain produces thought far faster than the mouth can speak or the fingers can type. These days I go back and edit things before I post them, and then I come back later and add to, or take away from, those same essays, to bring them up to what I know now.
There is a face I wear that says I am paying attention.
Jung called that face the persona: the mask turned toward the world, “a compromise between individual and society as to what a man should appear to be,” and not the thing standing behind it (Jung, 1966, para. 246). It is not a lie, exactly. It is the part of me that learned what a room expects, and gave it. Every person reading this owns one, and most of the time it is a kindness.
But pulling it off does not reveal the shadow. That is the mistake I made for years, and it is the mistake my own subtitle invites. Taking off the mask only stops the shadow from having somewhere to hide.
What is behind mine has never held still long enough to be named.
ADHD, to me, seemed to be the silly little devil that kept zipping around for no particular reason at all. Sometimes to the past. Sometimes to the future. Sometimes this caused depression. Sometimes anxiety. Sometimes those caused a relapse.
I cannot explain why I fell down the mountain so many times. I can only testify to how I climbed back out.
Register seam · Studied
A short one. The little devil brings friends, and someone has counted them.
In one clinical sample of adults with ADHD, more than six in ten had another psychiatric condition at some point in their lives, and about 44 percent met the criteria for insomnia disorder (Fadeuilhe et al., 2021).6 Anxiety and depression walk alongside it at rates I recognize from the inside.
But notice that the arrow does not have to point the way I want it to. ADHD is associated with insomnia, not proven to cause it. And in that same study, the adults who had been on stable treatment longer had less insomnia, not more, which is one more reason not to read my metaphor as advice.
If this is your life, take it to someone who can put a name to it. Not an essay. A person, with a license.
Register seam · Experienced
And now the part I actually came here to say.
The mirrored scale
Picture the balance scale from the last essay, needle pointing up. To the left is the past, to the right the future. The now is the middle, where you should be.
ADHD is quick little unexplainable jerks between the two.
This next part is hard to explain. Imagine that scale. Then imagine another one, mirrored over the top of it. It means the same thing: left, past; right, future.
But.
The lower scale is rooted in anxiety and depression. The mirrored one is rooted in the unknown. In the Self, not the ego.
It is not just you. It is everything else.
On the mirrored scale, the left, the past, is no longer depression and madness. It is reminiscence. Good memory. Balance the needle again. Think of the good things behind you.
And here I have to stop and say something plainly, because I was about to write a sentence that wasn’t true.
I was going to tell you to reject the bad memories at face value, and that Jung had said something similar.
Jung said close to the opposite. “No one can become conscious of the shadow without considerable moral effort,” he wrote, and becoming conscious of it means “recognizing the dark aspects of the personality as present and real” (Jung, 1951/1968a, para. 14). The series you are holding is named for that instruction. You turn toward. You do not turn away.
The evidence agrees with him in its own flat way: tell someone not to think of a white bear, and the bear gets louder. That rebound has been measured (Wegner et al., 1987; Wegner, 1994).
So let me be precise about what I actually do, because it is not suppression, and I nearly mislabeled my own practice.
I do not reject the memory.
I reject its authority.
Face it, and tell it no.
The memory stays. It stays integrated, it stays mine, I have already turned toward it across four other essays and I am not taking that back. What changes is that it no longer gets to decide which way the needle points. That is not denial. It is the withdrawal of a permission I never meant to grant.
Jung has a name for the part of this I can actually defend. He called it the transcendent function: holding the tension between the conscious attitude and what rises against it out of the unconscious, without letting either side win, until a third thing appears that neither could have made alone (Jung, 1969, paras. 131–193).
The needle moves right on this mirrored scale, and that is dreams. Possibilities. Premonitions. Not anxiety, not rooted in the ego, the I, but rooted in the Self, the greater good.
The hourglass
So where do we stand?
Picture both needles pointing up, but mirrored, so that they point at each other. You stand between them. That is the explanatory gap of your own life.
Now draw an X over that image. You stand at the crossing of the two lines, which is also exactly the place where the two needles fail to touch. Figure 1 is what I see when I close my eyes.
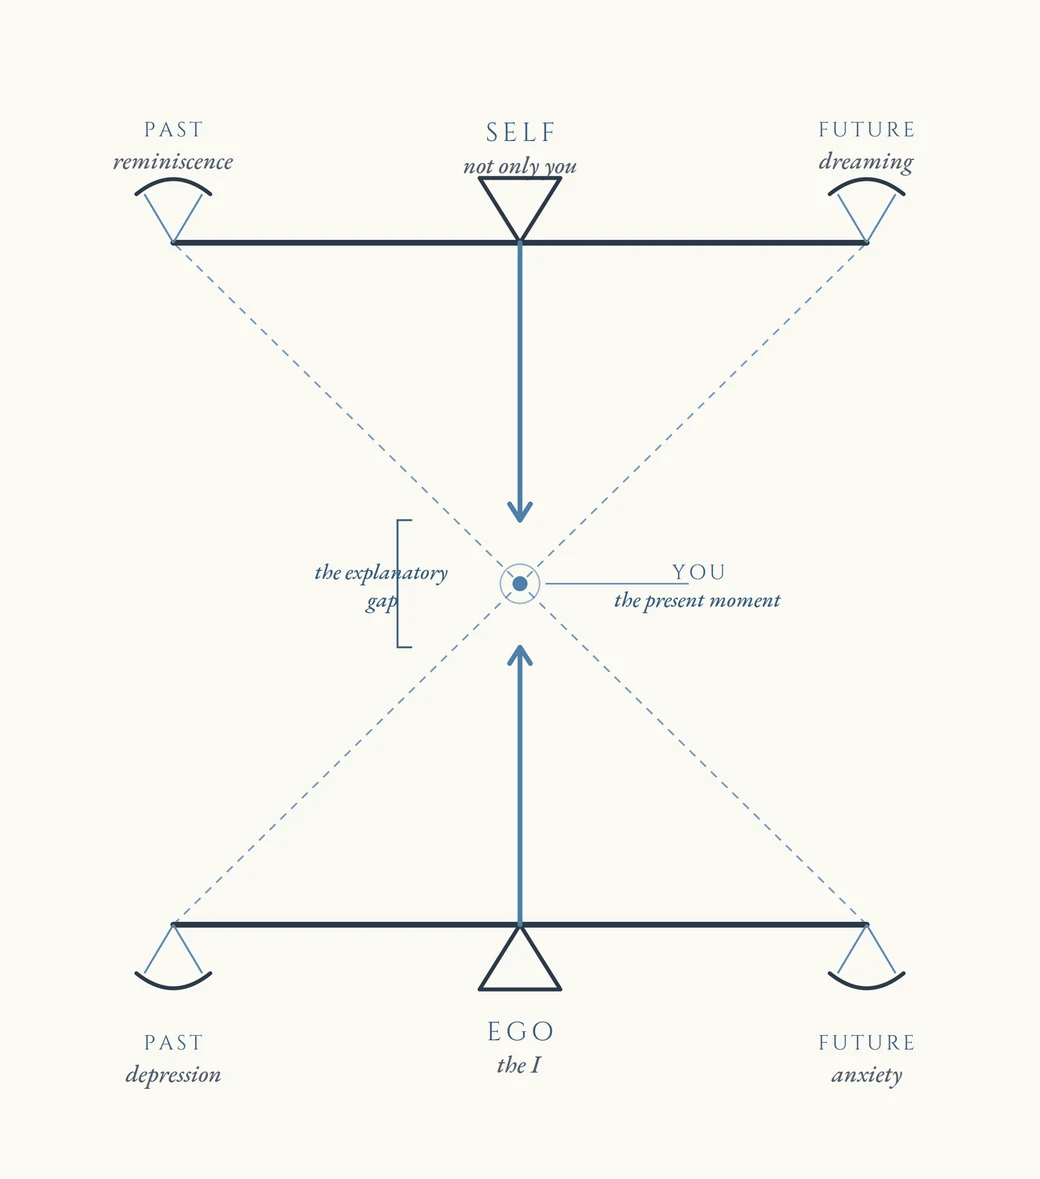
Kind of looks like an hourglass, doesn’t it.
Let me explain.
You look toward the past, and it can make you depressed. But it can also make you happy. Thinking about the things that matter. Remembering the things that are important: the ones that carve and shape an ego that lasts, and the ones that keep us whole instead of fragmented.
You look toward the future, and it can make you anxious. But it can also make you a dreamer. An idea machine. A think tank. The creativity flows when the needle moves this way, for me.
Look at the last few months of my life. What words can explain a complete hundred-and-eighty-degree turn in my path? Only the simple understanding of my own explanatory gap.
Understanding this place, to me, is understanding what makes you you. It is what shapes your ego. Pasts that happened that you need to let go of. Pasts you should not forget. Futures you should not worry about. Futures you should hold close to your heart to stay focused.
Focused.
How does one do that, living under this needle?
Flip the hourglass.
Stop living in the past and the future, and just live. You will be amazed what comes out.
For me, this was the last step that unlocked a meditational balance in my brain that would take a million years to explain on paper. So for now, picture the flipped hourglass.
Register seam · Studied
Because I am about to tell you that stillness helped, and you should know what is actually known about that.
There is a literature here, and it is friendlier than I expected without being a promise. In a randomized trial, mindfulness-based cognitive therapy added to usual treatment reduced clinician-rated ADHD symptoms in adults, compared with usual treatment alone (Janssen et al., 2019). A recent meta-analysis reports moderate improvements in symptoms and daily functioning; reviews of emotion regulation are more tentative, and the methods across the field are still uneven (Kim & Jung, 2025; López-Pinar et al., 2020; Poissant et al., 2019).
A promising companion. Not a cure, and not a replacement for anything.
Register seam · Experienced
Mine again.
Imagine you were not worried about the future, or the past, and were concerned only with the moment. Because any given moment of any individual’s experience is what matters most to that individual.
If that sentence makes you want to argue with me, good. Argue with it. But notice who is doing the arguing, and notice that the voice telling you this will never work for you has been wrong about you before.
Try it. Believe in yourself first, and then in the sentence.
And if you try it and nothing moves, that is not a verdict on how hard you believed. It means this particular door was not yours. There are other doors. Some of them have professionals standing behind them, and that is not a lesser door. It is only one I cannot open from here.
Watch what happens when you start replacing the darkness with light.
Register seam · Studied
One more thing, and then I will stop. This one is about children, and it is not about me at all.
The child, and the calendar
There is a finding I cannot stop thinking about.
In the American states that use September 1 as the school-entry cutoff, children born in August (the youngest in their class by nearly a full year) are diagnosed with ADHD at a rate about 34 percent higher than their classmates born in September: 85 per ten thousand against 64. They are treated more, too: 53 per ten thousand against 40. The effect does not appear in states without that cutoff. It does not appear for asthma, or diabetes, or obesity. Just this (Layton et al., 2018).7
Read that again. For some number of children, the difference between a diagnosis and no diagnosis is which side of an arbitrary line on a calendar they happened to be born on.
I do not conclude from this that childhood ADHD is a misunderstanding. That is not what the finding says. ADHD is among the most heritable conditions in psychiatry; twin studies put it at around 74 percent (Faraone & Larsson, 2019). And left alone, it costs children real things.
What the finding says is smaller, and sadder, and harder to shake. Sometimes we look at a younger child being younger, and we see a disorder.
The calendar is an adult’s line. A child does not draw it. A child only gets measured against it.
This is where my larger theory lives, the one this whole series is quietly built on: children are not born carrying these weights. They inherit them from us. Some of it, honestly, is inherited the old way, in the blood, and I will not pretend the twin studies away. But a gene handed down by a parent is still an inheritance from an adult. And the rest comes from the world we hand them. Children who spent their earliest months in severely depriving institutions show a pattern of inattention and overactivity that, for many, was still there in their twenties (Kennedy et al., 2016).8 In adoptive families, where parent and child share no genes at all, a rearing mother’s hostility predicts the child’s later ADHD symptoms, and part of that hostility is drawn out of her by the child’s own restless temperament (Harold et al., 2013). The child brings the spark. The adult decides whether it becomes a fire or a hearth. And the loop runs both ways, which is exactly why it is ours to break, not theirs.
Jung put it in one line I’d hang over every classroom door: “If there is anything that we wish to change in our children, we should first examine it and see whether it is not something that could better be changed in ourselves” (Jung, 1954, para. 287).9
Here is what the guidelines say about the youngest children. For preschoolers, the American Academy of Pediatrics recommends behavioral treatment first, with parents trained to manage behavior and classrooms adjusted to the child, before anything else is considered (Wolraich et al., 2019).10 Behavior first. That is the profession saying what this essay has been saying.
And what happens? Roughly 54 percent of American children with current ADHD are taking medication. About 44 percent received behavioral treatment in the past year. And about 30 percent, nearly one in three, received no ADHD treatment at all (Danielson et al., 2024). Across states, as the CDC puts it, “as ADHD diagnoses went up, the percentage of children receiving behavioral treatment for ADHD went down,” and “access to getting the right care and support may also affect such differences” (Centers for Disease Control and Prevention, n.d., Overview and Children’s Access to ADHD Care sections; Danielson et al., 2022).
That is not a profession that does not believe in the harder thing. That is a system that mostly cannot reach it. Shortages. Cost. Waiting lists. Insurance.
We reach for the pill because the pill is what is in reach.
I used to think this happened because nobody was interested in doing the harder thing. Medicate and forget. I was wrong, and the numbers are what corrected me. The failure is not a lack of caring. It is a lack of reach. And reach is something adults build, or don’t.
And I want to be careful with the thing you may be expecting me to say next: that the medication is what costs a child their crayons. The evidence does not support it. The most careful review of ADHD and creativity found no overall negative effect of stimulants on creativity (Hoogman et al., 2020). Whatever the pill asks for, it does not appear to ask for that.
The same review found something I like better anyway. The link between ADHD and divergent thinking (the fluency, the flexibility, the originality, the thoughts arriving faster than the fingers) turns up in people who carry the traits but not the diagnosis, more than in people with the diagnosis itself.
The trait, not the disorder. The needle, not the fall.
Which is, I think, the entire essay.
Register seam · Experienced
Nothing below this line is a finding. It is only what I think is true.
My philosophy, and it is philosophy, not evidence, is that a child arrives already creative. Nobody hands it to them. It is simply what a child is doing when they are being a child, and it looks, from the outside, an awful lot like not paying attention. What gets handed to them is everything after: the calendar, the classroom built for stillness, the tired adult, the waiting list, the name.
Jung wrote that the child, as a symbol, stands for “the strongest, the most ineluctable urge in every being, namely the urge to realize itself” (Jung, 1968b, para. 289). I think of that every time I see a kid who will not sit still.
And some adults, having lost the thread of it somewhere between then and now, need help to find their way back. For an adult, sometimes that help is a pill. There is no shame anywhere in that sentence. I have spent this entire essay trying to make sure there isn’t.
Mirrored creativity, unmanaged.
That is all I have ever meant by any of this.
Again, this is not a replacement for medical advice. It is meant to be held as a companion. An explanation. From one mirror to another.
A note on the seams
This essay makes no clinical claim. Where it touches the empirical literature, it reports what the literature reports, including the parts that cut against the author’s own metaphors. Where it leaves the literature, it says so, out loud, on the page. The hourglass in Figure 1 is a drawing of an argument and nothing more. The author is a student, not a clinician, and the distance between those two things is the subject of every seam in this essay.
♥
Notes
1. The study followed good responders only, which matters for the paragraph after this one.
2. Forty-one of the sixty-eight patients who needed more than 60 mg a day developed tolerance; none of the ninety-eight below that dose did.
3. The sample was eighteen previously unmedicated adults; the link to how it feels off the medication is the authors’ suggestion, not their finding.
4. Seventeen percent kept both medication and dose; mean methylphenidate dose rose from 30.5 to 34.4 mg a day, about 13 percent.
5. Average daily methylphenidate doses at the end of treatment were about 31 mg in the combined group and about 38 mg with medication management alone.
6. Lifetime psychiatric comorbidity was 63.1 percent; current comorbidity was 49.2 percent.
7. The data are commercial insurance claims.
8. Among adoptees with more than six months of severe deprivation, 29.3 percent met criteria for ADHD at ages 22 to 25, against 3.8 percent of those with little or none.
9. On the parents’ “unlived life” as what weighs on a child most, see Turning Toward the Subconscious.
10. For preschoolers (age four to the sixth birthday) the guideline puts parent training in behavior management and classroom interventions first; for children six to eleven it pairs FDA-approved medication with those behavioral treatments.
References
Centers for Disease Control and Prevention. (n.d.). ADHD diagnosis and treatment varies from state to state. Retrieved October 22, 2026, from https://www.cdc.gov/adhd/articles/diagnosis-and-treatment-varies-from-state-to-state.html
Danielson, M. L., Claussen, A. H., Bitsko, R. H., Katz, S. M., Newsome, K., Blumberg, S. J., Kogan, M. D., & Ghandour, R. (2024). ADHD prevalence among U.S. children and adolescents in 2022: Diagnosis, severity, co-occurring disorders, and treatment. Journal of Clinical Child & Adolescent Psychology, 53(3), 343–360. https://doi.org/10.1080/15374416.2024.2335625
Danielson, M. L., Holbrook, J. R., Bitsko, R. H., Newsome, K., Charania, S. N., McCord, R. F., Kogan, M. D., & Blumberg, S. J. (2022). State-level estimates of the prevalence of parent-reported ADHD diagnosis and treatment among U.S. children and adolescents, 2016 to 2019. Journal of Attention Disorders, 26(13), 1685–1697. https://doi.org/10.1177/10870547221099961
Fadeuilhe, C., Daigre, C., Richarte, V., Grau-López, L., Palma-Álvarez, R. F., Corrales, M., & Ramos-Quiroga, J. A. (2021). Insomnia disorder in adult attention-deficit/hyperactivity disorder patients: Clinical, comorbidity, and treatment correlates. Frontiers in Psychiatry, 12, Article 663889. https://doi.org/10.3389/fpsyt.2021.663889
Faraone, S. V., & Larsson, H. (2019). Genetics of attention deficit hyperactivity disorder. Molecular Psychiatry, 24(4), 562–575. https://doi.org/10.1038/s41380-018-0070-0
Handelman, K., & Sumiya, F. (2022). Tolerance to stimulant medication for attention deficit hyperactivity disorder: Literature review and case report. Brain Sciences, 12(8), Article 959. https://doi.org/10.3390/brainsci12080959
Harold, G. T., Leve, L. D., Barrett, D., Elam, K., Neiderhiser, J. M., Natsuaki, M. N., Shaw, D. S., Reiss, D., & Thapar, A. (2013). Biological and rearing mother influences on child ADHD symptoms: Revisiting the developmental interface between nature and nurture. Journal of Child Psychology and Psychiatry, 54(10), 1038–1046. https://doi.org/10.1111/jcpp.12100
Hoogman, M., Stolte, M., Baas, M., & Kroesbergen, E. (2020). Creativity and ADHD: A review of behavioral studies, the effect of psychostimulants and neural underpinnings. Neuroscience & Biobehavioral Reviews, 119, 66–85. https://doi.org/10.1016/j.neubiorev.2020.09.029
Humphreys, K. L., Eng, T., & Lee, S. S. (2013). Stimulant medication and substance use outcomes: A meta-analysis. JAMA Psychiatry, 70(7), 740–749. https://doi.org/10.1001/jamapsychiatry.2013.1273
Janssen, L., Kan, C. C., Carpentier, P. J., Sizoo, B., Hepark, S., Schellekens, M. P. J., Donders, A. R. T., Buitelaar, J. K., & Speckens, A. E. M. (2019). Mindfulness-based cognitive therapy v. treatment as usual in adults with ADHD: A multicentre, single-blind, randomised controlled trial. Psychological Medicine, 49(1), 55–65. https://doi.org/10.1017/S0033291718000429
Jung, C. G. (1954). The development of personality (R. F. C. Hull, Trans.; Collected Works of C. G. Jung, Vol. 17). Princeton University Press.
Jung, C. G. (1966). Two essays on analytical psychology (R. F. C. Hull, Trans.; 2nd ed.; Collected Works of C. G. Jung, Vol. 7). Princeton University Press.
Jung, C. G. (1968a). Aion: Researches into the phenomenology of the self (R. F. C. Hull, Trans.; 2nd ed.; Collected Works of C. G. Jung, Vol. 9, Pt. 2). Princeton University Press. (Original work published 1951)
Jung, C. G. (1968b). The archetypes and the collective unconscious (R. F. C. Hull, Trans.; 2nd ed.; Collected Works of C. G. Jung, Vol. 9, Pt. 1). Princeton University Press.
Jung, C. G. (1969). The structure and dynamics of the psyche (R. F. C. Hull, Trans.; 2nd ed.; Collected Works of C. G. Jung, Vol. 8). Princeton University Press.
Kennedy, M., Kreppner, J., Knights, N., Kumsta, R., Maughan, B., Golm, D., Rutter, M., Schlotz, W., & Sonuga-Barke, E. J. S. (2016). Early severe institutional deprivation is associated with a persistent variant of adult attention-deficit/hyperactivity disorder: Clinical presentation, developmental continuities and life circumstances in the English and Romanian Adoptees study. Journal of Child Psychology and Psychiatry, 57(10), 1113–1125. https://doi.org/10.1111/jcpp.12576
Kim, H.-H., & Jung, N.-H. (2025). Mindfulness-based interventions for adults with ADHD: A systematic review and meta-analysis. Medicine, 104(37), Article e44308. https://doi.org/10.1097/MD.0000000000044308
Layton, T. J., Barnett, M. L., Hicks, T. R., & Jena, A. B. (2018). Attention deficit–hyperactivity disorder and month of school enrollment. New England Journal of Medicine, 379(22), 2122–2130. https://doi.org/10.1056/NEJMoa1806828
López-Pinar, C., Martínez-Sanchís, S., Carbonell-Vayá, E., Sánchez-Meca, J., & Fenollar-Cortés, J. (2020). Efficacy of nonpharmacological treatments on comorbid internalizing symptoms of adults with attention-deficit/hyperactivity disorder: A meta-analytic review. Journal of Attention Disorders, 24(3), 456–478. https://doi.org/10.1177/1087054719855685
MTA Cooperative Group. (1999). A 14-month randomized clinical trial of treatment strategies for attention-deficit/hyperactivity disorder. Archives of General Psychiatry, 56(12), 1073–1086. https://doi.org/10.1001/archpsyc.56.12.1073
Page, T. F., Pelham, W. E., III, Fabiano, G. A., Greiner, A. R., Gnagy, E. M., Hart, K. C., Coxe, S., Waxmonsky, J. G., Foster, E. M., & Pelham, W. E., Jr. (2016). Comparative cost analysis of sequential, adaptive, behavioral, pharmacological, and combined treatments for childhood ADHD. Journal of Clinical Child & Adolescent Psychology, 45(4), 416–427. https://doi.org/10.1080/15374416.2015.1055859
Pelham, W. E., Jr., Fabiano, G. A., Waxmonsky, J. G., Greiner, A. R., Gnagy, E. M., Pelham, W. E., III, Coxe, S., Verley, J., Bhatia, I., Hart, K., Karch, K., Konijnendijk, E., Tresco, K., Nahum-Shani, I., & Murphy, S. A. (2016). Treatment sequencing for childhood ADHD: A multiple-randomization study of adaptive medication and behavioral interventions. Journal of Clinical Child & Adolescent Psychology, 45(4), 396–415. https://doi.org/10.1080/15374416.2015.1105138
Poissant, H., Mendrek, A., Talbot, N., Khoury, B., & Nolan, J. (2019). Behavioral and cognitive impacts of mindfulness-based interventions on adults with attention-deficit hyperactivity disorder: A systematic review. Behavioural Neurology, 2019, Article 5682050. https://doi.org/10.1155/2019/5682050
Quinn, P. D., Chang, Z., Hur, K., Gibbons, R. D., Lahey, B. B., Rickert, M. E., Sjölander, A., Lichtenstein, P., Larsson, H., & D’Onofrio, B. M. (2017). ADHD medication and substance-related problems. American Journal of Psychiatry, 174(9), 877–885. https://doi.org/10.1176/appi.ajp.2017.16060686
Ross, D. C., Fischhoff, J., & Davenport, B. (2002). Treatment of ADHD when tolerance to methylphenidate develops [Letter to the editor]. Psychiatric Services, 53(1), 102. https://doi.org/10.1176/appi.ps.53.1.102
Safer, D. J., & Allen, R. P. (1989). Absence of tolerance to the behavioral effects of methylphenidate in hyperactive and inattentive children. The Journal of Pediatrics, 115(6), 1003–1008. https://doi.org/10.1016/S0022-3476(89)80759-0
Safren, S. A., Sprich, S., Mimiaga, M. J., Surman, C., Knouse, L., Groves, M., & Otto, M. W. (2010). Cognitive behavioral therapy vs relaxation with educational support for medication-treated adults with ADHD and persistent symptoms: A randomized controlled trial. JAMA, 304(8), 875–880. https://doi.org/10.1001/jama.2010.1192
Smith, C., Walker, H., Parlatini, V., & Cortese, S. (2026). Tolerance and tachyphylaxis to medications for attention-deficit/hyperactivity disorder (ADHD): A systematic review of empirical studies. CNS Drugs, 40(4), 549–563. https://doi.org/10.1007/s40263-025-01263-8
Swanson, J. M., Arnold, L. E., Molina, B. S. G., Sibley, M. H., Hechtman, L. T., Hinshaw, S. P., Abikoff, H. B., Stehli, A., Owens, E. B., Mitchell, J. T., Nichols, Q., Howard, A., Greenhill, L. L., Hoza, B., Newcorn, J. H., Jensen, P. S., Vitiello, B., Wigal, T., Epstein, J. N., . . . MTA Cooperative Group. (2017). Young adult outcomes in the follow-up of the multimodal treatment study of attention-deficit/hyperactivity disorder: Symptom persistence, source discrepancy and height suppression. Journal of Child Psychology and Psychiatry, 58(6), 663–678. https://doi.org/10.1111/jcpp.12684
U.S. Food and Drug Administration. (2025). Ritalin (methylphenidate hydrochloride) tablets: Prescribing information (Revised February 2025). https://nctr-crs.fda.gov/fdalabel/services/spl/set-ids/d6fb2750-cdab-4749-ba0d-7534840a5892/spl-doc
Vitiello, B., Severe, J. B., Greenhill, L. L., Arnold, L. E., Abikoff, H. B., Bukstein, O. G., Elliott, G. R., Hechtman, L., Jensen, P. S., Hinshaw, S. P., March, J. S., Newcorn, J. H., Swanson, J. M., & Cantwell, D. P. (2001). Methylphenidate dosage for children with ADHD over time under controlled conditions: Lessons from the MTA. Journal of the American Academy of Child & Adolescent Psychiatry, 40(2), 188–196. https://doi.org/10.1097/00004583-200102000-00013
Wang, G.-J., Volkow, N. D., Wigal, T., Kollins, S. H., Newcorn, J. H., Telang, F., Logan, J., Jayne, M., Wong, C. T., Han, H., Fowler, J. S., Zhu, W., & Swanson, J. M. (2013). Long-term stimulant treatment affects brain dopamine transporter level in patients with attention deficit hyperactive disorder. PLOS ONE, 8(5), Article e63023. https://doi.org/10.1371/journal.pone.0063023
Wegner, D. M. (1994). Ironic processes of mental control. Psychological Review, 101(1), 34–52. https://doi.org/10.1037/0033-295X.101.1.34
Wegner, D. M., Schneider, D. J., Carter, S. R., & White, T. L. (1987). Paradoxical effects of thought suppression. Journal of Personality and Social Psychology, 53(1), 5–13. https://doi.org/10.1037/0022-3514.53.1.5
Wilens, T. E., Faraone, S. V., Biederman, J., & Gunawardene, S. (2003). Does stimulant therapy of attention-deficit/hyperactivity disorder beget later substance abuse? A meta-analytic review of the literature. Pediatrics, 111(1), 179–185. https://doi.org/10.1542/peds.111.1.179
Wolraich, M. L., Hagan, J. F., Jr., Allan, C., Chan, E., Davison, D., Earls, M., Evans, S. W., Flinn, S. K., Froehlich, T., Frost, J., Holbrook, J. R., Lehmann, C. U., Lessin, H. R., Okechukwu, K., Pierce, K. L., Winner, J. D., Zurhellen, W., & Subcommittee on Children and Adolescents With Attention-Deficit/Hyperactive Disorder. (2019). Clinical practice guideline for the diagnosis, evaluation, and treatment of attention-deficit/hyperactivity disorder in children and adolescents. Pediatrics, 144(4), Article e20192528. https://doi.org/10.1542/peds.2019-2528
CC BY 4.0 · ORCID 0009-0009-8618-398X · DOIs MINTED ON DEPOSIT
© 2026 JAMISON TODD JOHNSON · LEGIBLE TRACES LLC
Banner artwork Katsushika Hokusai, Sparrows and Chrysanthemums (c. 1830s), The Metropolitan Museum of Art. Public domain or CC0 — full list in the image credits.